

CASE REPORTS

A CASE OF TUBAL ECTOPIC PREGNANCY
Leelavathi Muthupalaniappen MMed(FamMed UKM), Tong Seng Fah MMed(FamMed UKM), Hazizi Hassan MBBS, Amilia Hazreena Hamidon MBChB
Department of Family Medicine, Universiti Kebangasaan Malaysia
A healthy 27 year old Para 3 presenting with abnormal menstruation without a period of amenorrhoea was diagnosed to have left tubal ectopic pregnancy after vaginal examination and abdominal ultrasonography. The case illustrates the need for careful history taking and the need for considering ectopic pregnancy in women in the reproductive age group, who have abnormal menstruation even if they are on contraception.
Keywords: Ectopic pregnancy
Leelavathi M, Tong SF, Hazizi H, Amilia-Hazreena H. A case of tubal ectopic pregnancy. Malaysian Family Physician. 2006;1(1):25-26
INTRODUCTION
Ectopic pregnancy is a potentially fatal emergency condition if early diagnosis is missed.1,2 The multitude of presentations to the primary care physician on first contact can be misleading in the absence of a high index of suspicion. The presentations vary widely from being asymptomatic to haemodynamically compromised.2 This case illustrates a woman who has been on contraception without the classical symptoms of ruptured ectopic pregnancy.
CASE REPORT
A 27 year old Para 3 whose last child was delivered 2 years ago, presented to Pusat Perubatan Primer (Primary Care Centre) on the 4th of January 2006 with a complaint of heavy prolonged menstruation. Her last normal menstrual period was on the 7th of November 2005. Her menstrual cycle had always been regular with normal flow. The current menstrual flow started on the 7th of December and prolonged until the date of first consultation at the clinic. On further questioning, she admitted that she had initially taken treatment from another clinic to “increase” flow of her menstruation when she experienced scanty flow during the first three days of this cycle. Upon treatment her menstruation became heavy and prolonged and hence she sought a second opinion. There were no other complaints and the patient denied any pain or discomfort in the abdomen.
She has been married for nine years and had three spontaneous vaginal deliveries. She was on combined oral contraceptive pills started a year ago and claimed to be
compliant with medication. There was no history of over-the-counter or prescribed medication taken during the last menstrual cycle. There were no significant past medical, surgical or gynaecological problems.
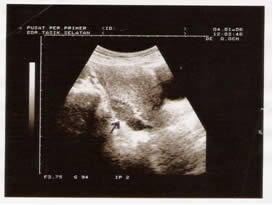
On examination she appeared comfortable and there were no signs of anaemia. Her blood pressure was 125/70 mmHg with a pulse rate of 85/min. Abdominal examination revealed mild tenderness over the lower abdomen. Vaginal examination excluded local causes of vaginal bleeding. On digital examination there was tenderness at the posterior fornix. Urine pregnancy test was positive. This was complemented by an empty uterine cavity with the presence fluid in the pouch of Douglas (arrow, Figure 1). Haemoglobin count was 12.3 x 10³ g/L and total white cell count was 7.5 x 10⁹g/L.
Figure I. Sagital section of transabdominal pelvic ultrasound image
<< Page 1 | 2 >>